


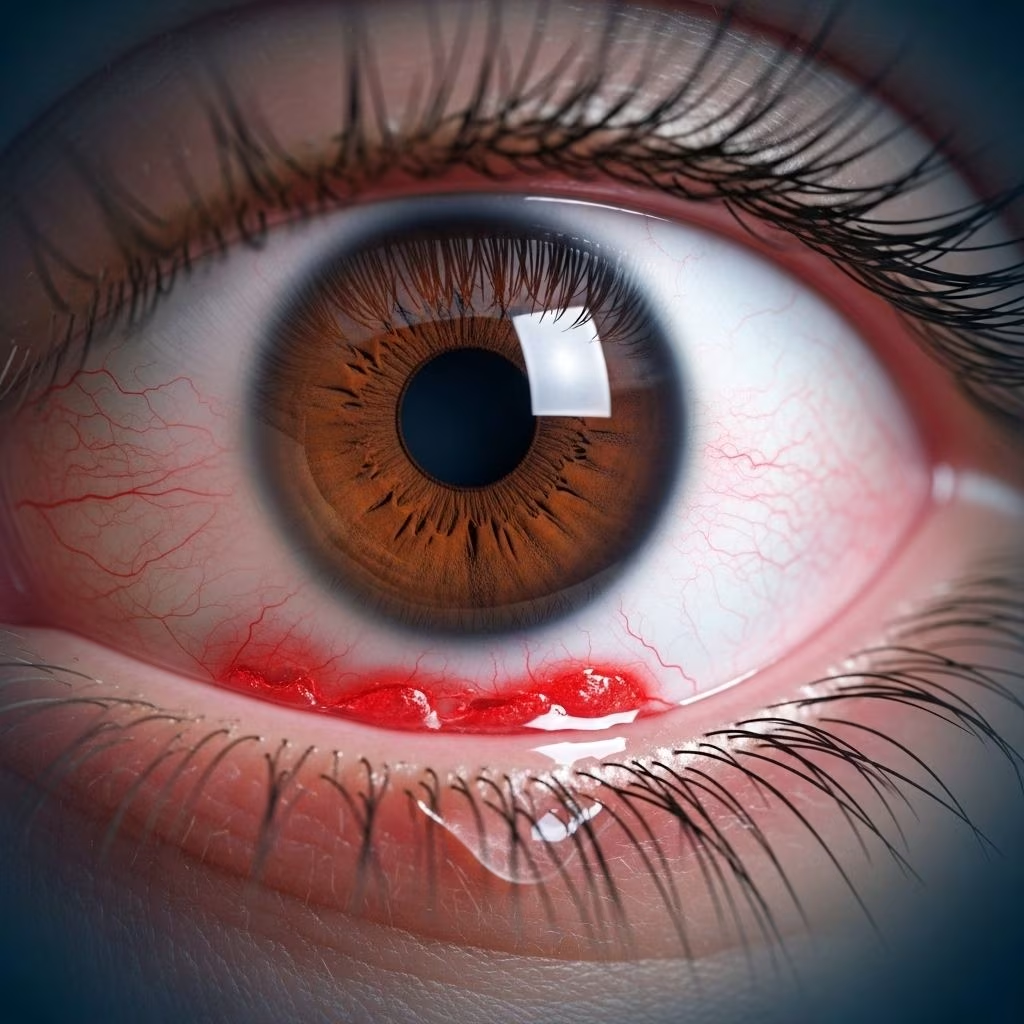
Acute Hemorrhagic Conjunctivitis: An In-Depth Overview
Acute hemorrhagic conjunctivitis (AHC) is a sudden-onset, highly contagious eye infection characterized by painful, red eyes and visible bleeding under the conjunctiva. Although AHC shares some features with typical viral conjunctivitis (“pink eye”), it is distinguished by dramatic subconjunctival hemorrhage and rapid symptom progression. AHC remains an international public health concern due to its ease of transmission, frequent outbreaks, and lack of specific treatment options.
This article provides a comprehensive look at its causes, symptoms, transmission, diagnostic approach, complications, prevention, and current evidence-based management.
What Is Acute Hemorrhagic Conjunctivitis?
AHC is a variant of viral conjunctivitis caused primarily by enterovirus 70 and a strain of coxsackievirus A24, with rare involvement of adenovirus type II. First identified in Ghana in the late 1960s, the disease has now been reported worldwide, including outbreaks across Asia, Africa, the Caribbean, and North America.
The conjunctiva, a thin membrane lining the eyelid and covering the white of the eye (sclera), becomes inflamed when infected, leading to severe redness and bleeding underneath.
Main Symptoms of Acute Hemorrhagic Conjunctivitis
AHC has a rapid and dramatic onset, typically developing within hours to a few days of exposure. Early symptoms can resemble those of traditional viral conjunctivitis, but quickly escalate. Key features include:
- Intensely red, swollen eyes (due to inflammation and hemorrhage)
- Subconjunctival hemorrhaging: bright red patches under the surface of the eye as blood vessels rupture
- Ocular pain and discomfort
- Excessive tearing (epiphora)
- Mucous discharge from the eyes
- Occasional blurred vision
- Periorbital and eyelid swelling; in severe cases, the eyelids may not close properly
- Photophobia (extreme sensitivity to light)
- Preauricular lymphadenopathy (swelling of the lymph nodes near the ear)
- Rare systemic symptoms such as fever and malaise
Most cases resolve without complications, but approximately 1 in 10,000 patients may experience polio-like paralysis known as radiculomyelitis, usually with enterovirus 70 infection.
How is AHC Transmitted?
AHC spreads easily and rapidly through direct and indirect contact. The main transmission routes are:
- Person-to-person contact (e.g., shaking hands, touching eyes)
- Contaminated surfaces and objects (fomites)
- Sharing towels, bedding, or personal care items
- Swimming pools and communal facilities
The viruses responsible for AHC are resilient and can thrive in crowded conditions, making outbreaks common in schools, workplaces, and healthcare settings. Infectious viral particles are present in eye secretions; individuals are most contagious in the initial days following symptom onset.
Causes: Viruses Behind Acute Hemorrhagic Conjunctivitis
AHC is mainly caused by:
- Enterovirus 70
- Coxsackievirus A24 variant
- Rarely, adenovirus type II
These viruses belong to the Picornaviridae family, and outbreaks often follow a seasonal pattern, especially in tropical and subtropical regions. Epidemic spread can occur within days, affecting large populations due to the virus’s stability and the highly contagious nature of the disease.
Diagnosis: Recognizing AHC
Diagnosis of AHC is primarily clinical, based on a combination of recent symptom onset, dramatic eye redness, and characteristic subconjunctival hemorrhage. Other forms of conjunctivitis (particularly bacterial, allergic, or non-hemorrhagic viral) typically lack the profound bleeding seen in AHC.
Key steps in the diagnostic process include:
- Detailed medical history, including possible exposure to infected individuals
- Physical eye examination, noting swelling, redness, discharge, and hemorrhage
- Distinguishing from other conjunctival conditions, such as epidemic keratoconjunctivitis, adult inclusion conjunctivitis, and atopic keratoconjunctivitis
Laboratory confirmation by conjunctival swab and RT-PCR testing (reverse transcription polymerase chain reaction) for viral RNA is available but rarely performed due to practical limitations, rapid disease course, and non-sight-threatening nature.
Complications and Risk Factors
- Pseudomembrane formation: In rare cases, patients may develop a whitish pseudomembrane on the conjunctiva, which should be removed to prevent scarring and contracture.
- Polio-like paralysis (radiculomyelitis): Exceptionally rare but serious, occurs in 1 in 10,000 cases—usually linked to enterovirus 70 infection.
- Symblepharon: When membrane removal is not thorough, scarring may cause the inner eyelid to stick to the eyeball.
- Superinfection: Secondary bacterial infection is possible, especially in immunocompromised individuals or if eye hygiene is poor.
How Long Does AHC Last?
Acute hemorrhagic conjunctivitis is self-limited, usually resolving within five to seven days. However, subconjunctival hemorrhages and swelling may persist for up to two weeks. During active illness, patients are highly contagious and should take precautions to avoid spreading the infection.
Treatment and Management of AHC
Currently, no specific antiviral therapy exists for AHC; treatment focuses on symptom relief and prevention of complications. Most physicians recommend the following approaches:
- Palliative therapy: Cool compresses applied to the eyes reduce swelling and discomfort.
- Ophthalmic lubricants: Artificial tears soothe irritation and dryness.
- Pain management: Over-the-counter analgesics (acetaminophen, ibuprofen) for pain and fever.
- Proper eye hygiene: Regular handwashing and cleaning of contaminated surfaces.
Antibiotics have no effect as the cause is viral; however, in certain cases, physicians use a combination of topical antibiotics and corticosteroids to:
- Relieve severe symptoms (inflammation, swelling)
- Reduce risk of superinfection (bacterial secondary infection)
Note: Some clinicians discourage steroid use due to possible corneal superinfection risk, but combined therapy with a broad-spectrum antibiotic may be considered when symptoms are severe or pseudomembrane is present.
Membrane management: If pseudomembranes form, careful removal (sometimes under local anesthesia) is recommended to prevent scarring or loss of eyelid function.
Prevention and Public Health Measures
- Early notification: Patients and communities should be informed to prevent alarm and promote precaution.
- Hand hygiene: Frequent handwashing is crucial to prevent person-to-person transmission.
- Avoid sharing personal items: Towels, linens, and cosmetics should not be shared during active infections.
- Disinfection: Clean high-touch surfaces like doorknobs and bathroom fixtures.
- Isolation during contagious period: Infected individuals should avoid close contact and public gatherings until symptoms resolve.
Currently, no vaccine is available for AHC. The most effective control strategy remains strict adherence to hygiene and avoidance of eye contact with contaminated surfaces.
Outlook and Prognosis
| Aspect | Typical Course | Comments |
|---|---|---|
| Onset | Sudden, within hours-days after exposure | Rapid progression, often affecting both eyes |
| Duration | Usually 5–7 days | Subconjunctival hemorrhage may last two weeks |
| Complications | Rare (membrane/scarring, paralysis) | Majority recover fully without long-term effects |
| Contagiousness | Very high initially | Take hygiene precautions during illness |
| Recurrence | Uncommon | No lasting immunity; repeat episodes possible |
When to Seek Medical Care
- If you experience severe eye pain, vision loss, or symptoms beyond seven days
- If symptoms worsen rapidly or are accompanied by fever and neurological symptoms (weakness, paralysis)
- If signs of secondary infection develop
Most cases can be managed at home with supportive care, but consultation with an eye health professional is advisable when symptoms are severe or atypical.
Frequently Asked Questions (FAQs) about Acute Hemorrhagic Conjunctivitis
What makes AHC different from regular “pink eye” (viral conjunctivitis)?
AHC causes prominent subconjunctival bleeding, rapid symptom onset, and often more severe pain and swelling than standard viral conjunctivitis. It is also more contagious and can lead to rare but serious complications.
How long does AHC last?
Symptoms usually resolve in 5 to 7 days, but visible bleeding or swelling may persist for up to 2 weeks.
Is AHC dangerous?
Most cases are benign and self-limited. Rarely, patients develop severe complications, including polio-like paralysis or vision impairment.
Can AHC be prevented?
There is no vaccine. Prevention depends on good hygiene, avoiding close contact during outbreaks, and not sharing personal items.
Are antibiotics ever needed?
Not for the viral infection itself, but topical antibiotics may be used in combination with corticosteroids to prevent bacterial complications or when symptoms are severe and risk of superinfection exists.
Is it safe to remove membrane from the eye?
This should only be done by a medical professional, usually under local anesthesia, to prevent scarring and preserve eyelid function.
Key Takeaways
- AHC is a viral eye infection with dramatic onset and highly contagious nature.
- Symptoms include red, painful eyes, and visible bleeding under the conjunctiva.
- No specific cure; management is supportive and focused on symptom relief.
- Strict hygiene and early isolation are critical to controlling outbreaks.
- Complications are rare, but medical care should be sought for severe or persistent symptoms.
References
- Wikipedia: Acute Hemorrhagic Conjunctivitis
- Review of Optometry: The Other Other Viral Infection
- PubMed: Acute Hemorrhagic Conjunctivitis
- VisualDx: Acute Hemorrhagic Conjunctivitis
References
- https://en.wikipedia.org/wiki/Acute_hemorrhagic_conjunctivitis
- https://www.reviewofoptometry.com/article/the-other-other-viral-infection
- https://pubmed.ncbi.nlm.nih.gov/1309404/
- https://www.visualdx.com/visualdx/diagnosis/acute+hemorrhagic+conjunctivitis?diagnosisId=53989&moduleId=21
- https://my.clevelandclinic.org/health/diseases/17713-subconjunctival-hemorrhage
- https://www.mayoclinic.org/diseases-conditions/subconjunctival-hemorrhage/symptoms-causes/syc-20353826


