


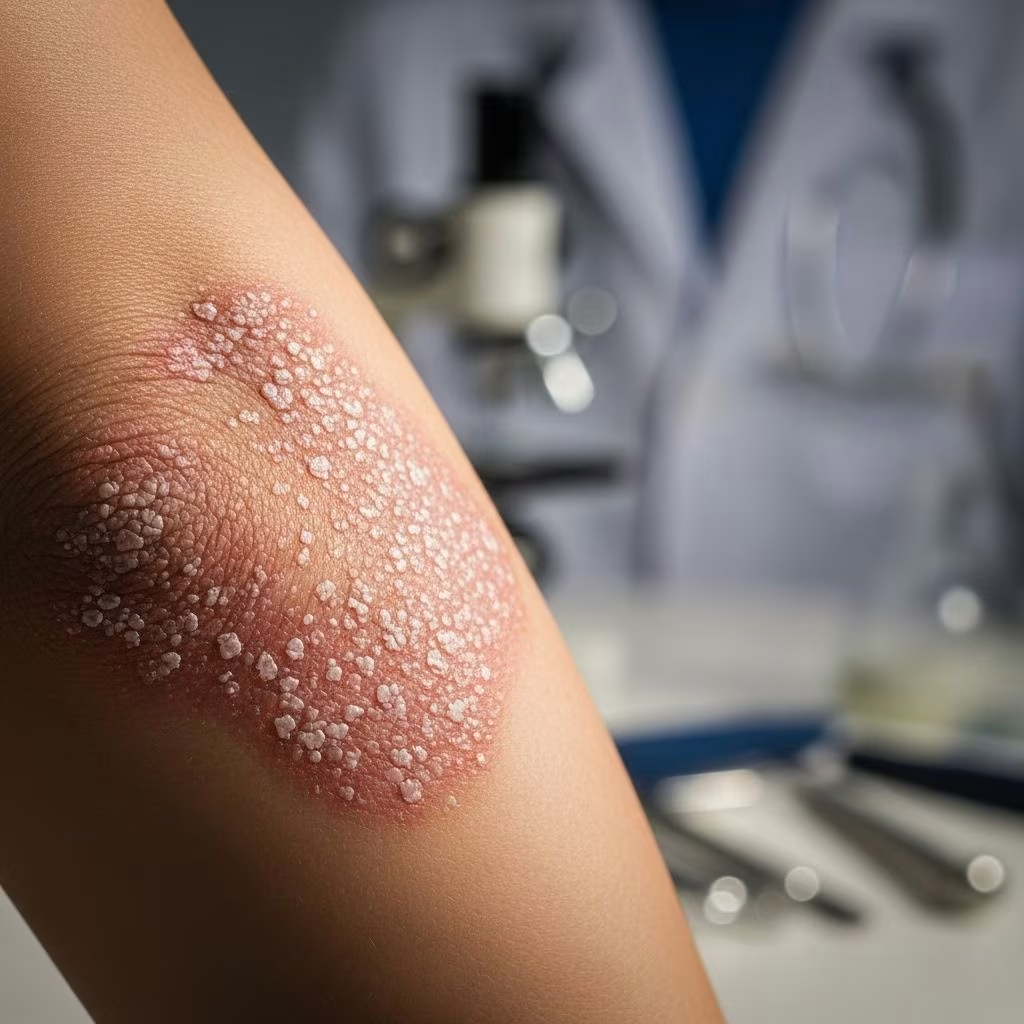
Psoriasis affects millions worldwide, presenting as a chronic inflammatory skin condition that significantly impacts quality of life. While numerous treatment options exist, a substantial proportion of patients develop resistance to conventional therapies, leaving them frustrated and seeking alternatives. Treatment-resistant psoriasis, particularly affecting the palms and soles, poses unique challenges for both patients and clinicians. Two time-tested therapeutic agents—coal tar and methotrexate—continue to demonstrate remarkable efficacy even in cases where modern biologics fail to deliver results.
Understanding how these established treatments work, their optimal application methods, and their role in managing stubborn psoriasis cases provides valuable insights for patients struggling with this persistent condition. This comprehensive exploration examines the mechanisms, clinical evidence, and practical applications of coal tar and methotrexate in treating psoriasis that refuses to respond to standard interventions.
Understanding Treatment-Resistant Psoriasis
Treatment-resistant psoriasis represents a particularly challenging subset of this chronic skin disorder. Patients with this condition fail to respond adequately to first-line therapies and may experience diminishing returns from treatments that initially provided relief. The palmoplantar variant, affecting the hands and feet, proves especially debilitating despite involving relatively small body surface areas. This localized presentation can severely impair daily activities, employment opportunities, and social interactions.
The resistance mechanism involves multiple factors including genetic predisposition, immune system variations, previous treatment history, and the specific psoriasis subtype. Patients may develop tolerance to medications over time, requiring escalation to more potent or alternative therapeutic approaches. The chronic inflammatory nature of psoriasis means that sustained treatment is often necessary, yet long-term use of many medications raises concerns about cumulative toxicity and adverse effects.
Palmoplantar psoriasis exemplifies the refractory nature of certain psoriasis presentations. The thick stratum corneum of palmar and plantar skin creates a formidable barrier to topical medication penetration, reducing treatment effectiveness. Additionally, these areas experience constant friction and trauma, potentially exacerbating symptoms and interfering with healing. These challenges necessitate innovative approaches that can overcome anatomical barriers while minimizing systemic side effects.
Coal Tar: A Time-Tested Therapeutic Agent
Coal tar has served as a cornerstone psoriasis treatment for over a century, earning its place through consistent efficacy and an excellent safety profile. This complex mixture of thousands of organic compounds derived from coal processing exerts multiple beneficial effects on psoriatic skin. Despite its somewhat archaic reputation, coal tar remains highly relevant in modern dermatology, particularly for patients who have exhausted other options.
Mechanism of Action
Coal tar works through several complementary mechanisms that collectively reduce psoriasis symptoms. The substance suppresses epidermal DNA synthesis, effectively slowing the accelerated cell turnover characteristic of psoriatic plaques. This antiproliferative effect helps normalize the skin’s renewal cycle, reducing the excessive scaling and thickening that defines the condition. Additionally, coal tar demonstrates anti-inflammatory properties that help calm the immune-mediated inflammation driving psoriasis progression.
The photosensitizing effects of coal tar provide another therapeutic dimension. When combined with ultraviolet light therapy, coal tar enhances treatment efficacy through the Goeckerman regimen, a classical approach still employed in specialized treatment centers. The substance also exhibits antimicrobial properties that may help prevent secondary infections in compromised skin.
Clinical Evidence and Efficacy
Research consistently demonstrates coal tar’s effectiveness in psoriasis management. In controlled trials examining palmoplantar psoriasis, 6 percent crude coal tar achieved good responses in 76.5 percent of patients, significantly outperforming control treatments. This impressive response rate validates coal tar’s continued use despite the availability of newer agents. The medication proves particularly valuable for patients who cannot tolerate or access more expensive biological therapies.
Studies comparing coal tar with other topical agents reveal its competitive performance. When evaluated against topical corticosteroids and calcipotriene, coal tar demonstrates comparable or superior efficacy in certain patient populations. Its safety profile allows for extended use without the adverse effects associated with prolonged corticosteroid application, such as skin atrophy and tachyphylaxis.
Formulations and Application Methods
Modern coal tar preparations come in various concentrations and formulations designed to balance efficacy with cosmetic acceptability. Available as ointments, creams, lotions, shampoos, bath oils, and soaps, these diverse options allow treatment customization based on lesion location and patient preferences. Higher concentrations generally provide greater therapeutic benefit but may prove less cosmetically acceptable due to odor and staining properties.
For palmoplantar psoriasis, ointment formulations under occlusion enhance penetration through the thick stratum corneum. Overnight application maximizes contact time while minimizing interference with daily activities. Newer formulations attempt to reduce the characteristic tar odor and staining while maintaining therapeutic potency, improving patient compliance and satisfaction.
Methotrexate: Systemic Therapy for Severe Disease
Methotrexate stands as the first-line systemic treatment for moderate-to-severe plaque psoriasis, offering reliable efficacy combined with affordability. Originally developed as an antimetabolite for cancer treatment, methotrexate’s immunosuppressive and anti-inflammatory properties make it highly effective for psoriasis management. The medication addresses the systemic nature of psoriasis while providing relief for resistant cases that fail to respond to topical interventions alone.
Pharmacological Properties
Methotrexate functions as a folic acid antagonist, interfering with DNA synthesis and cell replication. At the doses used for psoriasis treatment, the drug primarily exerts immunomodulatory effects, suppressing activated T lymphocytes that drive the inflammatory cascade in psoriatic lesions. This mechanism addresses the underlying pathophysiology rather than merely treating surface symptoms, potentially providing more sustained disease control.
The medication demonstrates particular effectiveness for psoriatic arthritis and nail psoriasis, conditions often resistant to purely topical approaches. By systemically modulating immune function, methotrexate can simultaneously improve multiple manifestations of psoriatic disease, offering comprehensive management for patients with complex presentations.
Clinical Outcomes and Response Rates
Most patients receiving methotrexate for psoriasis observe significant improvement within four to six weeks of initiating therapy. The medication effectively treats severe psoriasis, psoriatic arthritis, and nail involvement, providing broad-spectrum benefit across various disease manifestations. Clinical studies document substantial symptom reduction and quality of life improvements in responding patients.
When compared with other systemic agents, methotrexate demonstrates competitive efficacy while maintaining superior cost-effectiveness. This economic advantage proves particularly important for patients in resource-limited settings or those without comprehensive insurance coverage. The extensive clinical experience accumulated over decades of use provides reassurance regarding long-term safety when appropriate monitoring protocols are followed.
Administration and Monitoring
Methotrexate is administered as a once-weekly oral dose in both adults and children, simplifying the dosing schedule and potentially improving adherence. The intermittent dosing pattern may also reduce cumulative toxicity compared with daily administration. Subcutaneous injection represents an alternative route for patients experiencing gastrointestinal side effects or absorption issues with oral formulations.
Regular monitoring is essential to detect potential hematological and hepatic complications early. Baseline laboratory evaluation followed by periodic reassessment of complete blood counts, liver function tests, and creatinine levels helps identify developing problems before they become serious. Folic acid supplementation typically accompanies methotrexate therapy to mitigate certain side effects while preserving therapeutic efficacy.
Innovative Delivery: Methotrexate Iontophoresis
Traditional topical methotrexate applications have yielded inconsistent results due to poor skin penetration. The medication’s molecular properties prevent adequate passive diffusion through intact skin, limiting effectiveness when simply applied to the surface. Iontophoresis offers an innovative solution by using electrical current to drive medication through the stratum corneum, enhancing delivery to target tissues while minimizing systemic exposure.
Technique and Application
Methotrexate iontophoresis employs low-level electrical current to facilitate drug penetration through the skin barrier. The procedure utilizes the injectable methotrexate formulation at a concentration of 50 mg per 2 ml, applied to affected areas through specialized electrodes. Initial protocols typically involve weekly sessions for four weeks, followed by biweekly maintenance treatments, totaling six sessions in the induction phase.
This delivery method specifically benefits palmoplantar psoriasis, where the anatomical barriers to topical penetration prove most challenging. By actively driving medication through the thickened stratum corneum, iontophoresis achieves therapeutic drug levels in target tissues without requiring systemic administration, potentially reducing the risk of adverse effects associated with oral or injectable methotrexate.
Comparative Efficacy Studies
Clinical trials directly comparing methotrexate iontophoresis with coal tar ointment demonstrate superior outcomes with the iontophoresis approach. In one pilot study involving 28 patients with palmoplantar psoriasis, both treatment modalities produced score reductions, but methotrexate iontophoresis achieved statistically significant greater improvement. Both erythema, scaling, induration, and fissuring scores decreased more substantially in the iontophoresis-treated areas compared with coal tar-treated control sites.
These findings suggest that enhanced drug delivery through iontophoresis overcomes the penetration limitations that previously hampered topical methotrexate efficacy. The technique combines the local targeting advantages of topical therapy with the potency of methotrexate, creating a hybrid approach particularly suited for localized resistant disease. The safety profile appears favorable, with minimal systemic absorption reducing concerns about cumulative toxicity.
Combination and Sequential Therapy Approaches
Modern psoriasis management increasingly recognizes that combination or sequential therapy strategies often outperform monotherapy, particularly for treatment-resistant cases. The complementary mechanisms of coal tar and methotrexate create opportunities for synergistic effects when used together or in carefully planned sequences. Understanding how to optimally combine these agents with other treatment modalities maximizes therapeutic outcomes while managing potential risks.
Coal Tar and Phototherapy
The Goeckerman regimen, combining coal tar application with ultraviolet B phototherapy, represents one of dermatology’s oldest and most effective combination treatments. The photosensitizing properties of coal tar enhance ultraviolet light penetration and efficacy, producing response rates that exceed either modality alone. This approach remains particularly valuable for extensive psoriasis or cases resistant to conventional topical therapies.
Modified versions incorporating narrowband UVB or targeted phototherapy provide similar benefits with improved convenience and reduced treatment time. Patients unable to access specialized phototherapy centers may benefit from coal tar application before controlled natural sunlight exposure, though this requires careful patient education regarding appropriate exposure duration and sun protection.
Integrating Systemic and Topical Approaches
For severe or widespread psoriasis with particularly resistant localized areas, combining systemic methotrexate with targeted coal tar application addresses disease at multiple levels. The systemic agent manages overall disease activity while the topical treatment provides additional benefit for stubborn plaques. This strategy proves especially useful for palmoplantar involvement accompanying more extensive body surface area disease.
Studies examining patients treated with both methotrexate and coal tar reveal improvements not only in skin manifestations but also in metabolic parameters. Research demonstrates favorable effects on adipokine levels and insulin resistance indices, suggesting these treatments may provide systemic benefits beyond dermatological improvement. These metabolic effects carry particular significance given the recognized association between psoriasis and cardiovascular risk factors.
Corticosteroid Combination Protocols
Short-term high-potency topical corticosteroids combined with coal tar or during methotrexate initiation can provide rapid symptom relief while the slower-acting agents reach therapeutic effectiveness. This approach manages patient expectations and discomfort during the initial treatment phase. Intermittent corticosteroid pulses may maintain control achieved with coal tar or methotrexate while minimizing steroid-associated adverse effects.
For palmoplantar disease specifically, comparing topical corticosteroids with coal tar against photochemotherapy reveals comparable effectiveness with different adverse effect profiles. Treatment selection should consider individual patient circumstances, including access to phototherapy facilities, tolerance for medication characteristics, and previous treatment responses.
Managing Treatment-Resistant Cases: A Systematic Approach
Successfully managing treatment-resistant psoriasis requires a methodical evaluation process followed by strategic intervention selection. Clinicians must determine whether apparent treatment failure represents true resistance, inadequate therapy duration, improper application technique, or secondary factors interfering with treatment response. This diagnostic clarity guides appropriate therapeutic modifications.
Initial Assessment and Optimization
Before escalating to more aggressive therapies, confirming that current treatments have been optimally utilized prevents premature abandonment of potentially effective agents. Many patients apply topical medications inconsistently or in insufficient quantities, undermining efficacy. Education regarding proper application techniques, expected timelines for improvement, and strategies for managing cosmetic concerns with coal tar improves outcomes with existing treatments.
Identifying and addressing contributing factors such as stress, infections, medications, or lifestyle factors that trigger or worsen psoriasis may restore responsiveness to previously ineffective treatments. Comprehensive patient assessment examines physical, psychological, and social dimensions that collectively influence disease expression and treatment response.
Therapeutic Algorithm
For mild-to-moderate localized disease, high-potency topical corticosteroids represent first-line therapy, used for limited duration to minimize adverse effects. When sustained treatment becomes necessary, transitioning to coal tar or calcipotriene provides continued benefit with improved safety profiles. Topical salicylic acid may be added to facilitate scale removal and enhance subsequent medication penetration.
More severe or recalcitrant disease warrants systemic intervention, with methotrexate serving as the preferred initial systemic agent given its established efficacy, safety profile, and affordability. The presence and pattern of psoriasis involvement beyond palmoplantar areas influences systemic agent selection, as does individual patient factors including comorbidities, medication tolerances, and treatment preferences.
When to Consider Biological Therapies
Biological agents including adalimumab, etanercept, infliximab, ixekizumab, secukinumab, and apremilast offer powerful alternatives when traditional systemic drugs prove inadequate. These targeted therapies demonstrate impressive efficacy rates in clinical trials and real-world practice. However, their substantial cost and potential for serious adverse effects reserve them for cases truly resistant to conventional approaches.
Interestingly, some evidence suggests coal tar retains effectiveness even in patients who have failed biological therapies, highlighting its unique mechanisms and continued relevance. This observation suggests that cycling through different therapeutic classes, including returning to older agents after biological failure, may restore treatment responsiveness in some patients.
Safety Considerations and Monitoring
While both coal tar and methotrexate demonstrate favorable benefit-risk profiles when used appropriately, understanding potential adverse effects and implementing proper monitoring protocols ensures safe long-term management. Patient education regarding warning signs and the importance of adherence to monitoring schedules prevents serious complications.
Coal Tar Safety Profile
Coal tar’s excellent long-term safety record provides reassurance for extended use. Concerns about carcinogenic potential, particularly regarding polycyclic aromatic hydrocarbons in coal tar, have been extensively investigated. Large epidemiological studies found no increased cancer risk after coal tar treatment in patients with psoriasis or eczema, even with prolonged use. This evidence supports coal tar’s continued role as a safe, effective psoriasis treatment option.
The primary limitations of coal tar relate to cosmetic acceptability rather than medical safety. The characteristic odor, potential for staining clothing and bedding, and messy application discourage some patients despite clinical effectiveness. Modern formulations address these concerns to varying degrees, though trade-offs between cosmetic elegance and therapeutic potency may exist.
Methotrexate Monitoring Requirements
Methotrexate’s potential for serious hematological and hepatic toxicity necessitates vigilant monitoring throughout treatment. Baseline evaluation establishes pretreatment status, while periodic reassessment detects developing abnormalities before they progress to clinically significant complications. Complete blood counts identify bone marrow suppression, while liver function tests and, when appropriate, imaging or biopsy assess hepatic health.
Folic acid supplementation mitigates certain methotrexate side effects without compromising therapeutic efficacy. Patients must understand the importance of weekly rather than daily dosing, as dosing errors represent a preventable cause of severe toxicity. Clear patient education and reminder systems help prevent these potentially catastrophic mistakes.
Drug Interactions and Contraindications
Methotrexate interacts with numerous medications, requiring careful medication reconciliation before initiation and vigilance when other drugs are added to a patient’s regimen. Nonsteroidal anti-inflammatory drugs, trimethoprim, and other medications affecting folate metabolism or renal function may enhance methotrexate toxicity. Alcohol consumption increases hepatotoxicity risk and should be minimized or avoided during treatment.
Absolute contraindications to methotrexate include pregnancy, severe hepatic or renal dysfunction, significant cytopenias, and immunodeficiency states. Relative contraindications requiring careful risk-benefit assessment include mild-to-moderate organ dysfunction, chronic infections, and certain comorbid conditions. Coal tar presents minimal contraindications, though application to acutely inflamed or broken skin may cause irritation.
Patient Perspectives and Quality of Life Impact
Treatment-resistant psoriasis profoundly affects psychological well-being, social functioning, and occupational capacity. Patients frequently experience depression, anxiety, and social isolation related to visible skin lesions and associated stigma. Palmoplantar involvement creates particular hardship given the essential role of hands and feet in daily activities, work performance, and social interactions. Understanding these impacts contextualizes the importance of achieving disease control.
Addressing Treatment Burden
The chronicity of psoriasis necessitates sustained treatment, creating ongoing burden from medication application, monitoring requirements, and lifestyle modifications. Coal tar’s cosmetic limitations and methotrexate’s monitoring needs represent treatment-related burdens that may affect adherence. Balancing efficacy against treatment burden requires individualized approaches acknowledging each patient’s unique circumstances, priorities, and tolerance for different types of inconvenience.
Shared decision-making processes that incorporate patient preferences, values, and practical considerations optimize treatment selection and enhance adherence. Some patients prefer the predictable safety profile and topical nature of coal tar despite cosmetic drawbacks, while others favor systemic methotrexate’s convenience of weekly dosing and absence of visible residue. Respecting these preferences while providing evidence-based guidance creates collaborative therapeutic relationships.
Long-term Management Strategies
Successful long-term psoriasis management requires sustainable approaches that patients can maintain indefinitely without accumulating toxicity or experiencing treatment fatigue. Maintenance regimens using lower-intensity interventions after achieving initial control may provide ongoing benefit with reduced burden. Intermittent therapy during flares, supplemented by careful monitoring for early recurrence signs, offers another strategy for certain patients.
Education empowers patients to recognize factors triggering their psoriasis and implement lifestyle modifications that complement pharmacological interventions. Stress management, smoking cessation, weight optimization, and moderation of alcohol consumption may improve treatment responsiveness and overall health outcomes. These non-pharmacological approaches deserve emphasis as adjuncts to medication-based strategies.
Frequently Asked Questions
Q: How long does it take to see results from coal tar treatment?
A: Most patients begin noticing improvement within two to four weeks of consistent coal tar application. Optimal results typically emerge after six to eight weeks of regular use. Response timing varies based on disease severity, formulation strength, and application consistency.
Q: Can methotrexate cure psoriasis permanently?
A: Methotrexate controls psoriasis symptoms but does not cure the underlying condition. Most patients require ongoing treatment to maintain improvement, though some achieve prolonged remission after treatment discontinuation. Psoriasis remains a chronic condition requiring long-term management strategies.
Q: Is coal tar safe for long-term use?
A: Yes, extensive research demonstrates that coal tar is safe for prolonged use in psoriasis treatment. Large epidemiological studies found no increased cancer risk even with long-term application, supporting coal tar as a safe maintenance therapy option.
Q: What are the most common side effects of methotrexate for psoriasis?
A: Common side effects include nausea, fatigue, and mild gastrointestinal upset. More serious but less common complications involve liver toxicity and bone marrow suppression, which regular monitoring helps detect early. Folic acid supplementation reduces many minor side effects.
Q: Can coal tar and methotrexate be used together?
A: Yes, combining systemic methotrexate with topical coal tar application is safe and may provide superior results compared with either treatment alone. This combination addresses psoriasis through complementary mechanisms, potentially benefiting patients with severe or resistant disease.
Q: Why does my psoriasis stop responding to treatments that previously worked?
A: Treatment resistance develops through various mechanisms including tachyphylaxis, changes in disease biology, development of antibodies to biological agents, or secondary factors interfering with treatment response. Addressing adherence issues, optimizing application techniques, or switching therapeutic classes often restores effectiveness.
Q: How does methotrexate iontophoresis differ from regular topical application?
A: Iontophoresis uses electrical current to actively drive methotrexate through the skin barrier, achieving much better penetration than passive diffusion. This enhanced delivery produces superior efficacy for localized disease, particularly on palms and soles where thick skin prevents adequate absorption of conventionally applied topicals.
Q: Are there any dietary restrictions while using methotrexate?
A: Alcohol should be minimized or avoided due to increased hepatotoxicity risk. Folic acid supplementation is recommended, though timing should be coordinated with methotrexate dosing. No specific foods require elimination, though maintaining good nutrition supports overall health and treatment tolerance.
References
- https://ijdvl.com/methotrexate-iontophoresis-versus-coal-tar-ointment-in-palmoplantar-psoriasis-a-pilot-study/
- https://onlinelibrary.wiley.com/doi/10.1111/ijd.16193
- https://pubmed.ncbi.nlm.nih.gov/24665910/
- https://pmc.ncbi.nlm.nih.gov/articles/PMC5363132/
- https://www.aafp.org/pubs/afp/issues/2000/0201/p725.html
- https://www.aad.org/public/diseases/psoriasis/treatment/medications/methotrexate
- https://dermnetnz.org/topics/guidelines-for-the-treatment-of-psoriasis
- https://www.healthline.com/health/psoriasis/why-your-psoriasis-treatment-is-not-working


